Patient guide
DVT clot removal: why an extensive clot needs more than blood thinners
Why a deep vein thrombosis (DVT) that extends beyond the thigh into the pelvic veins (iliofemoral DVT) does better with catheter-based clot removal than with blood thinners alone: long-term leg health, post-thrombotic syndrome, and what the trials show, with references.
Why treat an extensive clot directly, at a glance
- No open surgeryClot treated from inside the vein
- Veins open soonerBetter blood flow after treatment
- Faster reliefLess leg pain and swelling within days
- Healthier legsLess long-term leg damage
- Minimal blood lossClot removed by suction, not surgery
- Shorter hospital stayOften home in 1 to 2 days

Why a clot above the thigh needs more than blood thinners
Deep vein thrombosis (DVT) is a blood clot in a deep vein of the leg. Blood thinners are the foundation of treatment: they stop the clot growing and help the body break it down over time [1]. For a small clot in the calf or the thigh vein, that may be all that is needed.
A clot that extends above the thigh vein (the femoral vein) into the iliac veins of the pelvis is different. This is called iliofemoral DVT. These are the main veins that carry blood from the whole leg back to the heart, so when they are blocked the whole leg is affected. Blood thinners do not remove this clot. They leave the body to clear it, and often the vein stays blocked or damaged.
That is why iliofemoral DVT is the group where catheter-based clot removal matters most.
What happens with blood thinners alone
A study followed patients with iliofemoral DVT who were treated with blood thinners alone for at least five years. On follow-up scans, 38 legs were examined. 84% had leg swelling, 26% had skin damage, three developed leg ulcers, and 34% still had a blocked vein. Pain in the leg while walking (venous claudication) was seen in 18% of legs, all of them in patients whose clot involved several vein segments [6].
The affected legs were significantly more likely to show signs of post-thrombotic syndrome than the other leg. The authors concluded that standard blood thinners alone give unfavourable long-term outcomes in iliofemoral DVT, and that additional treatment should be considered [6].
Post-thrombotic syndrome (PTS) means long-term leg pain, swelling and heaviness after a DVT, and in severe cases skin changes and ulcers [3]. Preventing it is the main reason to remove the clot early.
Labropoulos et al., J Vasc Surg Venous Lymphat Disord 2026, 38 legs with iliofemoral DVT, follow-up of 5 years or more [6].
Why people choose catheter-based clot removal
People with an extensive clot often ask whether the clot itself can be removed instead of leaving it to the body. Here is what draws them to catheter-based treatment.
- It removes the clot directly, from inside the vein, under imaging guidance, with no open surgery.
- Veins open sooner: at six months the vein was open in 66% of treated patients against 47% with blood thinners alone [2].
- Minimal blood loss and a short stay with the newer devices: a mean blood loss of 60 mL with the Lightning Flash, and a median hospital stay of 2 days [9, 10].
- Faster relief: patients with iliofemoral DVT had a greater reduction in leg pain and swelling within 10 and 30 days [5].
- Healthier legs for the long term: post-thrombotic syndrome was 43% against 71% at five years in CaVenT [3].
- Fewer severe cases: severe post-thrombotic syndrome was 8.7% against 15% in the iliofemoral patients of ATTRACT [5].
- A short stay and a quick recovery. At Clinic Seven, most patients go home after 1 to 2 days and are back to normal activity in about a week.
What catheter-based treatment involves
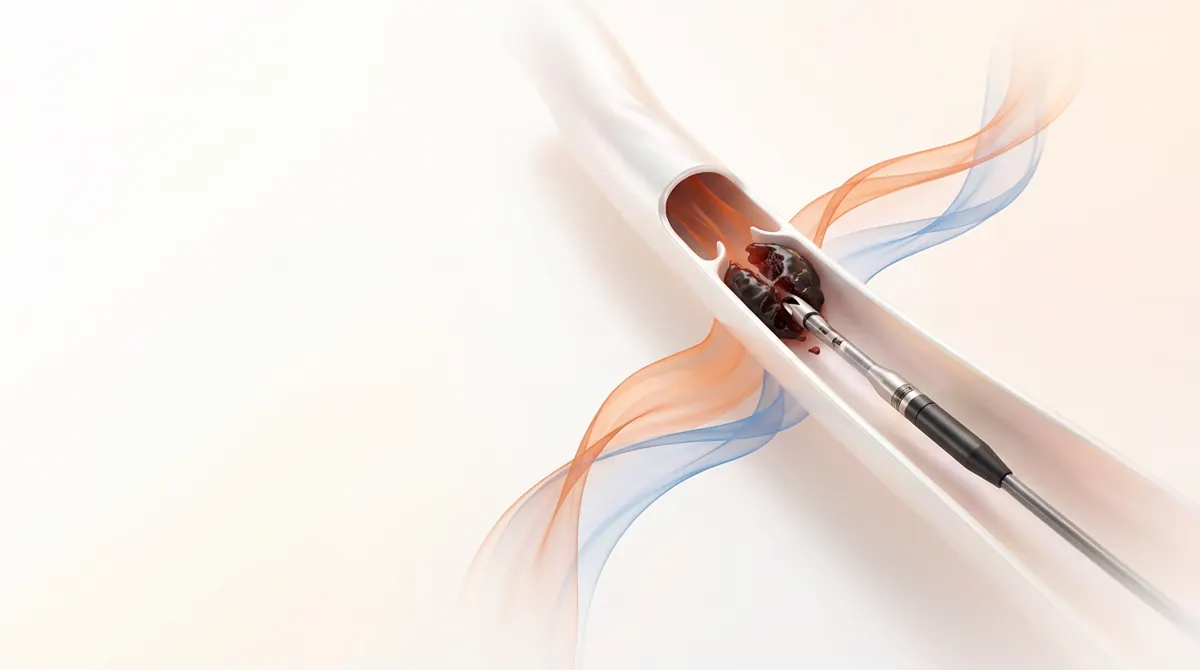
A thin catheter is passed into the clotted vein under imaging guidance. Clot-dissolving medicine such as alteplase is delivered directly into the clot, and in pharmacomechanical treatment a device also removes or breaks up the clot. A narrowed vein can then be opened with a stent [2, 4]. Clinic Seven uses the newer thrombectomy systems for this: AngioJet, and the Penumbra Lightning Flash and Lightning Bolt.
Blood thinners continue alongside the procedure, so you get the benefit of both [1].
The newer way: AngioJet and Penumbra Lightning Flash and Bolt
The older way of treating a large clot meant running clot-dissolving medicine through a catheter for many hours or days, often with a stay in intensive care. Newer thrombectomy devices take a different route. They remove the clot directly, by suction or by a high-pressure jet, so that most of the clot is cleared in a single session and the need for long drug infusions falls.
The AngioJet uses a high-speed saline jet to break up and draw out the clot. In the PEARL registry of 329 patients, 73% of procedures were completed in under 24 hours, major bleeding was not related to the device in any patient, and the authors noted it can potentially reduce the need for long drug infusions and intensive care [11].
The Penumbra Lightning system uses computer-assisted vacuum suction. In a series of 25 patients treated with the 16F Lightning Flash, every patient was treated in a single session with a mean blood loss of just 60 mL, no clot-dissolving drug was used, 88% of veins were still open at follow-up of 8 to 26 months, and there were no pulmonary emboli or device-related complications [9]. In another series of 24 patients treated with the Lightning 12 and Lightning Flash 16, the median hospital stay was 2 days, no complications occurred during the procedure, and the median Villalta score (a measure of long-term leg problems) was 1, which means little or no post-thrombotic syndrome [10].
- Minimal blood loss: a mean of 60 mL with the Lightning Flash [9].
- A short hospital stay: a median of 2 days in the Lightning series [10].
- Treatment in a single session, often without clot-dissolving drugs [9, 12].
- Low rates of long-term leg problems: 94% of 82 patients treated with AngioJet were free of post-thrombotic syndrome at a median follow-up of 25 months [13].
Abramowitz et al., Eur J Vasc Endovasc Surg 2024, 130 matched pairs, ClotTriever mechanical thrombectomy compared with the pharmacomechanical arm of ATTRACT [12].
What the randomised trials found
Two large randomised trials looked at adding catheter-based treatment to blood thinners. The results are strongest in patients whose clot reaches the iliac veins.
| Trial | Patients | What was found |
|---|---|---|
| CaVenT (Norway) | 209 with a first iliofemoral DVT, treated within 21 days | Post-thrombotic syndrome at 2 years: 41% with added treatment against 56% without [2]. At 5 years: 43% against 71% [3] |
| ATTRACT (USA), iliofemoral patients | 391 with a clot in the iliac or common femoral veins | Moderate-to-severe post-thrombotic syndrome 18% against 28%. Severe 8.7% against 15%. Faster relief of leg pain and swelling [5] |
CaVenT: a lasting protection for the legs
In CaVenT, 209 patients with a first-time iliofemoral DVT were treated within 21 days of symptoms. Adding catheter-directed treatment reduced post-thrombotic syndrome from 55.6% to 41.1% at 24 months, and the vein was open at six months in 66% of the treated group against 47% [2]. The benefit lasted. At five years post-thrombotic syndrome was 43% in the treated group and 71% in the standard group, so for about every four patients treated, one avoided long-term leg damage [3]. The authors concluded that added treatment should be considered for patients with a high proximal DVT and a low risk of bleeding [2].
Haig et al., Lancet Haematol 2016 [3]. 176 of 209 patients followed for 5 years.
ATTRACT: fewer severe cases in iliofemoral DVT
ATTRACT was the largest trial, with 692 patients [4]. Looking at the 391 patients whose clot involved the iliac or common femoral veins, pharmacomechanical treatment cut the share with moderate-to-severe post-thrombotic syndrome from 28% to 18%, and severe post-thrombotic syndrome from 15% to 8.7%. These patients also had a greater reduction in leg pain and swelling in the first 30 days, and a greater improvement in vein-specific quality of life over 24 months [5].
The message of the two trials together is clear: the patients with the most extensive clots gain the most from removing the clot.
Comerota et al., Circulation 2019, 391 patients with iliofemoral DVT [5].
What the specialist societies say
The Society of Interventional Radiology reviewed 84 studies and published 17 recommendations on acute iliofemoral DVT. It considers endovascular thrombus removal an acceptable treatment option in selected patients, alongside good general DVT care, careful assessment of risk, and close monitoring during and after the procedure [7].
How patients are selected
Selection is what makes catheter-based treatment work well. It is usually discussed when the clot is extensive and reaches the iliofemoral veins, symptoms are significant, the clot is recent (CaVenT treated patients within 21 days of symptom onset), and the risk of bleeding is low [2, 7]. As with any clot-dissolving treatment, bleeding is what the team watches for, so every patient is assessed carefully beforehand. For a small calf clot, blood thinners alone are the right treatment, and your team will say so.
Compression stockings are a separate question. In a placebo-controlled trial, stockings worn for two years did not prevent post-thrombotic syndrome after a first proximal DVT [8], which is why treating the clot itself matters for the right patients.
When to seek urgent care
If you have sudden swelling or pain in a leg, please see a doctor the same day. If you also have sudden breathlessness, chest pain or coughing blood, go to an emergency department immediately, because these can be signs the clot has reached the lungs. Starting treatment promptly protects you, and it also keeps catheter treatment available, because it is aimed at recent clots.
Questions to ask at your consultation
Bring your Doppler or CT venogram reports, medicine list and any recent blood tests, and ask:
- How far does my clot extend, and does it reach the iliac veins?
- Is blood thinner treatment alone enough for me, or would removing the clot protect my leg better?
- How soon do I need to be treated?
- What is my bleeding risk, and how will it be managed?
- What follow-up will I need, and for how long should I stay on blood thinners?
Frequently asked questions
- Are blood thinners enough for DVT?
- Blood thinners are the foundation of treatment and are enough for many smaller clots [1]. When a clot extends above the thigh vein into the pelvic veins, blood thinners alone often leave long-term problems: after five years, 84% of legs had swelling and 26% had skin damage in one study [6]. Removing the clot can protect the leg [3, 5].
- What is iliofemoral DVT?
- It is a clot that reaches the iliac veins in the pelvis and the common femoral vein at the top of the thigh. These are the main veins that carry blood out of the leg, so a blockage affects the whole leg. This is the group that benefits most from catheter-based clot removal [5, 7].
- Does clot removal prevent long-term leg damage?
- It lowers it. In CaVenT, post-thrombotic syndrome was 43% against 71% at five years [3], and in the iliofemoral patients of ATTRACT, moderate-to-severe post-thrombotic syndrome fell from 28% to 18% [5].
- How soon should treatment start?
- As early as possible. CaVenT treated patients within 21 days of symptom onset [2], and treatment is aimed at recent clots, so early assessment matters. Please see a doctor the same day if you notice sudden leg swelling or pain.
- What is the newest way to remove a DVT clot?
- Newer thrombectomy devices such as AngioJet and the Penumbra Lightning Flash and Lightning Bolt remove the clot directly, in a single session. Published series report minimal blood loss (a mean of 60 mL with the Lightning Flash) and short hospital stays (a median of 2 days) [9, 10], and AngioJet patients had a 94% freedom from post-thrombotic syndrome at a median follow-up of 25 months [13].
- What are the risks of catheter-based treatment?
- As with any clot-dissolving treatment, bleeding is the main thing the team watches for. Patients are assessed for bleeding risk beforehand, and treatment is done by an experienced team with imaging guidance [7].
- Where can I get DVT clot removal in Hyderabad?
- Dr. Nagateja Bonala offers catheter-based DVT treatment, including the AngioJet system, at Clinic Seven, Kukatpally. Please bring your Doppler or CT venogram reports to the consultation.
References
- Stevens SM, et al. Antithrombotic Therapy for VTE Disease: Second Update of the CHEST Guideline and Expert Panel Report. Chest. 2021;160(6):e545-e608. Read the source
- Enden T, et al. Long-term outcome after additional catheter-directed thrombolysis versus standard treatment for acute iliofemoral deep vein thrombosis (the CaVenT study): a randomised controlled trial. Lancet. 2012;379(9810):31-38. Read the source
- Haig Y, et al. Post-thrombotic syndrome after catheter-directed thrombolysis for deep vein thrombosis (CaVenT): 5-year follow-up results of an open-label, randomised controlled trial. Lancet Haematol. 2016;3(2):e64-e71. Read the source
- Vedantham S, et al. Pharmacomechanical Catheter-Directed Thrombolysis for Deep-Vein Thrombosis (ATTRACT). N Engl J Med. 2017;377(23):2240-2252. Read the source
- Comerota AJ, et al. Endovascular Thrombus Removal for Acute Iliofemoral Deep Vein Thrombosis. Circulation. 2019;139(9):1162-1173. Read the source
- Labropoulos N, et al. The long-term clinical impact of iliofemoral deep vein thrombosis. J Vasc Surg Venous Lymphat Disord. 2026 Sep. Read the source
- Vedantham S, et al. Society of Interventional Radiology Position Statement on the Endovascular Management of Acute Iliofemoral Deep Vein Thrombosis. J Vasc Interv Radiol. 2023;34(2):284-299.e7. Read the source
- Kahn SR, et al. Compression stockings to prevent post-thrombotic syndrome: a randomised placebo-controlled trial. Lancet. 2014;383(9920):880-888. Read the source
- Saleem T, et al. Computer-assisted vacuum aspiration mechanical thrombectomy with Lightning Flash allows broader clinical application, enhanced procedural safety, and improved clinical outcomes for the treatment of acute and subacute iliofemoral and central deep venous thrombosis. J Vasc Surg Cases Innov Tech. 2025. Read the source
- Gonzalez-Urquijo M, et al. Computer-assisted vacuum thrombectomy using Lightning 12 and Lightning Flash 16 in acute proximal lower extremity deep vein thrombosis. Phlebology. 2026 Jul. Read the source
- Garcia MJ, et al. Endovascular Management of Deep Vein Thrombosis with Rheolytic Thrombectomy: Final Report of the Prospective Multicenter PEARL Registry. J Vasc Interv Radiol. 2015;26(6):777-785. Read the source
- Abramowitz S, et al. Mechanical Thrombectomy vs. Pharmacomechanical Catheter Directed Thrombolysis for the Treatment of Iliofemoral Deep Vein Thrombosis: A Propensity Score Matched Exploratory Analysis of 12 Month Clinical Outcomes. Eur J Vasc Endovasc Surg. 2024 Apr. Read the source
- Forgo G, et al. Midterm clinical outcomes of mechanical versus rheolytic thrombectomy for iliofemoral or iliocaval deep vein thrombosis. J Vasc Surg Venous Lymphat Disord. 2026 May. Read the source
Want to discuss your options?
Speak with the Clinic Seven team.