Patient guide
Prostate artery embolization (PAE) for BPH: evidence
Why prostate artery embolization (PAE) is worth exploring for an enlarged prostate: proven symptom relief, no cutting, fewer side effects than TURP in a trial, results two years on, and who it suits.
Advantages over surgery at a glance
- Local anaesthesiaNo spinal or general anaesthesia
- No cutsNothing is removed
- 3x less likely to lose ejaculation16 in 100 men after PAE vs 52 in 100 after TURP, the usual operation
- Fewer urine flow problemsLower urethral stricture risk
- Lasting reliefMost men still do well years later



Who PAE is for
Benign prostatic hyperplasia (BPH) is an age-related enlargement of the prostate. It can cause a weak stream, frequent urination, getting up at night and a feeling of not emptying the bladder. Medication is usually the first step, and the trials below enrolled men whose symptoms had not settled with medicines or who preferred not to take them [2, 3, 5].
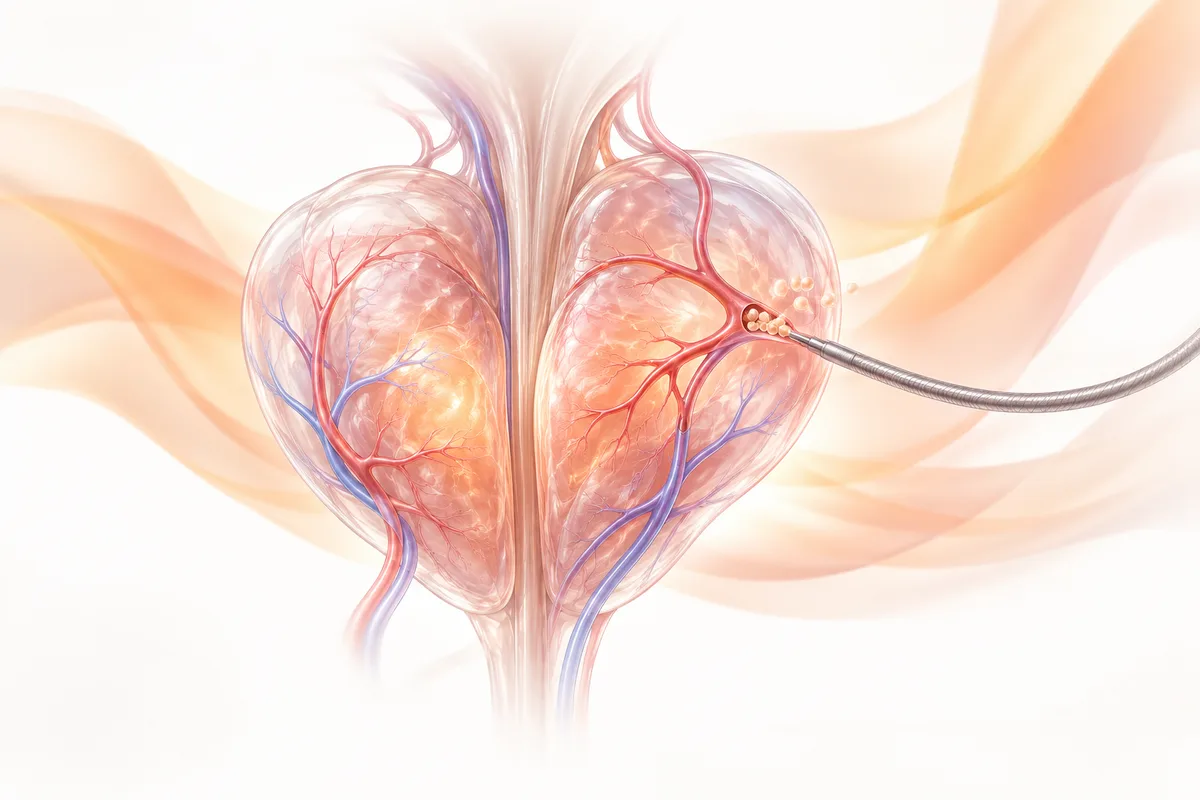
For those men the usual next step is a surgical procedure such as transurethral resection of the prostate (TURP). Prostate artery embolization (PAE) is a gentler option for selected men. A thin catheter is guided to the arteries that feed the prostate, and tiny particles are released to reduce the blood flow so the gland shrinks gradually and urinary symptoms ease.
Why PAE is worth exploring
If you have an enlarged prostate, you have more choices than tablets for life or a big operation. PAE is a proven, well-studied option, and it is worth a proper look. Here is why so many men explore it.
- No cutting or removal of prostate tissue, and local anaesthesia in the randomised trial [2].
- Fewer adverse events than TURP in that trial: 36 events against 70 [2].
- Proven to work: men who had real PAE improved by about 13 points more on their symptom score than men given a pretend procedure [3].
- Lasting relief: in 630 men, 81.9% had a good result at 1 to 3 years and 76.3% beyond 3 years, with no urinary incontinence or sexual dysfunction reported [5].
- A route for large prostates: in men with prostates over 100 mL, clinical success was 90% at one month and 72.4% out to 5.5 years [6].
- A quick recovery. At Clinic Seven, most patients are back to normal activity within a few days.
Advantages over surgery: what you can avoid
Compared with TURP and other prostate operations, PAE lets you avoid several of the burdens of surgery. These are the main ones.
- Spinal or general anaesthesia. PAE was performed under local anaesthesia in the randomised trial [2].
- Cutting and removal of prostate tissue through the urethra. PAE works from the arteries and removes nothing.
- A higher burden of adverse events: 36 events after PAE against 70 after TURP in the 12 weeks following treatment [2].
- Losing ejaculation completely. In one review TURP was associated with retrograde ejaculation in 50% to 70% of men, while PAE limits the rate [7]. In the Swiss randomised trial, 16% of men lost ejaculation completely after PAE compared with 52% after TURP, although some PAE men noticed weaker ejaculation [11]. Read our guide on sex life after prostate treatment.
- Concerns about erections and incontinence. No urinary incontinence or sexual dysfunction was reported in 630 men followed for up to 6.5 years [5], and PAE appeared to improve erectile function relative to open prostatectomy [4].
PAE compared with TURP
TURP removes prostate tissue through the urethra and is the traditional surgical operation for BPH. PAE offers a different route. In a randomised trial of 103 men in Switzerland, PAE was done under local anaesthesia, while TURP needed spinal or general anaesthesia [2].
| TURP | PAE | |
|---|---|---|
| Anaesthesia | Spinal or general [2] | Local anaesthesia [2] |
| Cutting or removal of tissue | Yes, through the urethra | None, treated from the arteries |
| Symptom score improvement (IPSS) | 10.8 points [2] | 9.2 points [2] |
| Adverse events | 70 events [2] | 36 events, about half as many [2] |
How much relief to expect
In the Swiss randomised trial, the average symptom score fell by 9.23 points after PAE at 12 weeks, and PAE was associated with fewer adverse events than TURP (36 events against 70) [2]. In an earlier randomised trial of 114 men, symptoms, quality of life, urine flow and prostate volume all improved significantly after PAE at every follow-up point up to 24 months [1].
Abt et al., BMJ 2018, randomised trial of 103 men [2].
Proof that PAE really works
Is it the treatment, or just hope? A trial set out to answer exactly that. Eighty men with severe symptoms, even on tablets, were split into two groups without being told which one they were in. Half had real PAE. Half had a pretend procedure with no embolization. Six months later the men who had real PAE were about 13 points better on their symptom score, and much happier with their quality of life. When the men from the pretend group were then given real PAE, they improved by about 13.6 points too [3]. The researchers concluded that the benefit is far greater than any placebo effect. This is a treatment that does what it says.
Results over the longer term
One large series followed 630 consecutive men for up to 6.5 years. The technical success rate was 98.1%, cumulative clinical success was 81.9% at 1 to 3 years and 76.3% beyond three years, and there were 2 major complications without lasting effects. No urinary incontinence or sexual dysfunction was reported [5]. In a separate series of 152 men with prostates larger than 100 mL, who would often be offered open surgery, clinical success was 90% at one month and 72.4% out to 5.5 years [6].
Pisco et al., J Vasc Interv Radiol 2016 [5, 6]. Single-centre series.
Two-year results from an international study
A prospective international study followed 478 men treated with PAE at several centres, with an average age of 70. In the 405 men treated for bothersome symptoms, the average symptom score fell from 21.8 before treatment to 9.3 at 3 months, 10.6 at 12 months and 11.2 at 24 months, and the quality-of-life score fell from 4.7 to 2.3. Erection scores were unchanged a year later (13.8 before, 13.9 after). Among the 73 men treated because they could not pass urine, 48 (66%) had the catheter out within 3 months and were still catheter-free at 24 months. About 1 in 9 men had any side effect (11.5%) and about 1 in 50 had a serious one (2.1%) [8]. This study had no comparison group.
What the specialist societies say
The Society of Interventional Radiology's 2026 practice guidance, written by a group of interventional radiologists, states that PAE has gained a place in multiple guidelines, including the American Urological Association's most recent, as a viable option for urine symptoms caused by BPH. It also sets out how to choose patients and how to do the procedure safely [9]. A 2026 review of the evidence adds that PAE offers lower procedural risk in medically high-risk men and early protection of sexual and bladder-control function, and that it is also used for stubborn prostate bleeding [10]. Like every treatment it has trade-offs. The same review notes that urine flow improves less and retreatment is more common than after TURP or laser enucleation, which is why we choose patients carefully [10].
Where PAE fits among your options
A systematic review of seven studies with 810 patients concluded that PAE is an emerging treatment option for men with symptomatic BPH who cannot undergo surgery or whose medical therapy has failed. PAE had fewer adverse events overall, and it appeared to improve erectile function relative to open surgery [4].
In short, PAE is a well-studied option for men who want relief of prostate symptoms through a gentler procedure that needs no cutting.
Who tends to suit which option
These are patterns from the studies, not rules. The right choice follows your symptoms, prostate size, scans and health.
- PAE is often discussed for men who want to avoid surgery or general anaesthesia, are less suited to an operation because of other medical conditions, or want to protect sexual function [2, 4, 5].
- Your specialist will review your prostate size, scans and symptoms to confirm whether PAE or another approach is best for you.
- Medication and monitoring remain appropriate for men with milder symptoms.
Questions to ask at your consultation
Bring your prostate ultrasound or MRI, PSA result and a list of your current medicines, and ask:
- Is my prostate size and anatomy suitable for embolization?
- How much improvement in symptoms is realistic for me, and how soon?
- How does PAE compare with TURP or other surgery for my situation?
- What is the plan if my symptoms do not settle?
- What follow-up and tests will I need afterwards?
Frequently asked questions
- How does PAE compare with TURP?
- In a randomised trial, PAE was done under local anaesthesia with no cutting, brought a 9.2-point symptom improvement at 12 weeks, and had about half as many adverse events as TURP (36 versus 70) [2]. Which option is best depends on your prostate and your priorities, and your consultation covers this in detail.
- Does PAE really work?
- Yes. In a trial where half the men were given a pretend procedure without knowing, the men who had real PAE improved by about 13 points more on their symptom score. When the pretend group then had real PAE, they improved by a similar amount [3].
- How long does the benefit of PAE last?
- In a series of 630 men, 81.9% had a good result at 1 to 3 years and 76.3% beyond 3 years, with follow-up of up to 6.5 years [5].
- Does PAE affect sexual function?
- In the 630-man series no sexual dysfunction or urinary incontinence was reported [5], and a systematic review found PAE appeared to improve erectile function relative to open surgery [4].
- Where can I get prostate artery embolization in Hyderabad?
- Dr. Nagateja Bonala offers prostate artery embolization at Clinic Seven, Kukatpally. Please bring your prostate ultrasound or MRI, PSA and medicine list to the consultation.
Check your prostate symptom score
References
- Gao YA, et al. Benign prostatic hyperplasia: prostatic arterial embolization versus transurethral resection of the prostate--a prospective, randomized, and controlled clinical trial. Radiology. 2014;270(3):920-8. Read the source
- Abt D, et al. Comparison of prostatic artery embolisation (PAE) versus transurethral resection of the prostate (TURP) for benign prostatic hyperplasia: randomised, open label, non-inferiority trial. BMJ. 2018;361:k2338. Read the source
- Pisco JM, et al. Randomised Clinical Trial of Prostatic Artery Embolisation Versus a Sham Procedure for Benign Prostatic Hyperplasia. Eur Urol. 2020;77(3):354-362. Read the source
- Altman R, et al. Comparing prostatic artery embolization to surgical and minimally invasive procedures for the treatment of benign prostatic hyperplasia: a systematic review and meta-analysis. BMC Urol. 2024;24(1):22. Read the source
- Pisco JM, et al. Medium- and Long-Term Outcome of Prostate Artery Embolization for Patients with Benign Prostatic Hyperplasia: Results in 630 Patients. J Vasc Interv Radiol. 2016;27(8):1115-22. Read the source
- Pisco J, et al. Prostate Embolization as an Alternative to Open Surgery in Patients with Large Prostate and Moderate to Severe Lower Urinary Tract Symptoms. J Vasc Interv Radiol. 2016;27(5):700-8. Read the source
- Couteau N, et al. Ejaculations and Benign Prostatic Hyperplasia: An Impossible Compromise? A Comprehensive Review. J Clin Med. 2021;10(24). Read the source
- Sapoval MR, et al. Two-Year Outcomes of Prostatic Artery Embolization for Symptomatic Benign Prostatic Hyperplasia: An International, Multicenter, Prospective Study. Cardiovasc Intervent Radiol. 2024. Read the source
- Mouli S, et al. Society of Interventional Radiology (SIR) 2026 Practice Guidance Document for Prostatic Artery Embolization. J Vasc Interv Radiol. 2026. Read the source
- Tawfellos G, et al. Prostatic Artery Embolization: A Contemporary Review of Efficacy, Safety, and Expanding Clinical Indications. Curr Urol Rep. 2026. Read the source
- Müllhaupt G, et al. Ejaculatory disorders after prostatic artery embolization: a reassessment of two prospective clinical trials. World J Urol. 2020. Read the source
Want to discuss your options?
Speak with the Clinic Seven team.