Patient guide
Pulmonary embolism: catheter thrombectomy with FlowTriever (Inari) and Lightning (Penumbra) devices
How large-bore catheter thrombectomy devices such as FlowTriever (Inari) and Lightning or Indigo (Penumbra) remove clots in the lung arteries, who they are used for, what the FLARE, EXTRACT-PE and PEERLESS studies show and the limits.
Catheter thrombectomy at a glance
- Removes the clotSuction through a catheter
- Avoids clot-busting drugsIn most patients
- No open surgeryThrough a vein in the groin or neck
- About 1-2 hoursFor most procedures
- Short ICU stayMany need little or none
- Selected patientsA team decides


What a pulmonary embolism is
A pulmonary embolism is usually a blood clot that travels from a leg or pelvic vein (see the deep vein thrombosis guide) to the arteries in the lungs. It strains the right side of the heart and reduces oxygen. It is grouped by severity: low-risk, intermediate-risk (stable, but with strain on the right heart), and high-risk (low blood pressure or shock). Treatment depends on this grade.
Usual treatment, and where catheters fit
Anticoagulant (blood-thinning) medicine is the foundation. For high-risk PE, clot-dissolving drugs given into a vein are the standard. The 2019 European guideline discusses catheter-directed treatment, either clot-dissolving drugs through a catheter or mechanical removal, for selected patients, particularly high-risk PE when thrombolysis has failed or cannot be used [1]. A pulmonary embolism response team, with a chest physician, cardiologist, intensivist and interventional radiologist, usually decides.
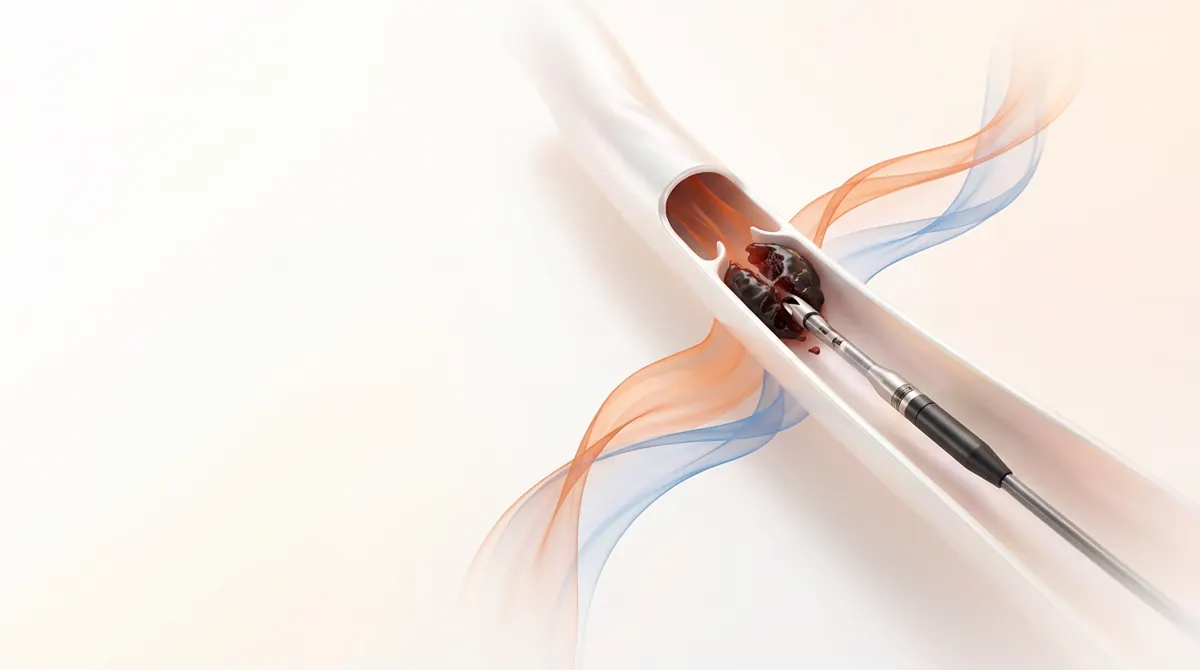
How large-bore thrombectomy works
These devices physically remove the clot instead of dissolving it.
- A sheath is placed in a large vein, usually at the groin, under local anaesthetic.
- A large catheter is guided through the right side of the heart into the lung arteries under X-ray.
- The clot is sucked out through the catheter, using a syringe or a continuous suction device. Examples are the FlowTriever system (Inari) and the Lightning or Indigo systems (Penumbra).
- Blood pressures and oxygen levels are monitored, and repeat imaging confirms clot removal.
- Blood thinners continue afterwards, and recovery is monitored in a high-dependency or intensive care unit.
What the studies show
In the FLARE single-arm trial, 106 patients with intermediate-risk PE had thrombectomy with the FlowTriever system. The right-to-left ventricle ratio fell by an average of 0.38 (25.1%) within 48 hours, and 41.3% needed no intensive care stay [2]. In the EXTRACT-PE single-arm trial, 119 patients treated with the Indigo system had a mean reduction in that ratio of 0.43, and thrombolytic drugs were avoided in 98.3% [3]. In the PEERLESS randomised trial, large-bore thrombectomy was compared with catheter-directed thrombolysis in intermediate-risk PE. Thrombectomy had fewer clinical deterioration events, less postprocedural intensive care use, shorter hospital stays and fewer readmissions, while deaths and major bleeding were similar [4].
| Study | Design | What it showed |
|---|---|---|
| FLARE [2] | Single arm, 106 patients, FlowTriever | RV/LV ratio fell by 0.38 in 48 hours, and 41.3% needed no ICU stay |
| EXTRACT-PE [3] | Single arm, 119 patients, Indigo aspiration | RV/LV ratio fell by 0.43, with thrombolytic drugs avoided in 98.3% |
| PEERLESS [4] | Randomised against catheter-directed thrombolysis | Fewer clinical deteriorations and less ICU use, with similar deaths and major bleeding |
Limits of the evidence
These trials mostly measure how much the strain on the heart improves and short-term safety. FLARE and EXTRACT-PE had no control group, and PEERLESS compared two catheter strategies, so none has shown that thrombectomy saves more lives than blood thinners alone. Trials are continuing. Large devices are not suited to every patient or lesion, for example very small branch clots or some anatomies. Device companies funded much of this research, which is why independent guidelines [1] and a multidisciplinary decision matter.
Risks
Risks include bleeding, injury to the heart or a lung artery, an abnormal heart rhythm, kidney injury from contrast dye, a drop in blood pressure during the procedure, and access site problems. Because the patient is often already unwell, thrombectomy is done in a hospital with intensive care, in a team that can handle these events.
Preventing another clot
The source clot, often in the legs, needs attention, and blood thinners usually continue for months. For patients who cannot take blood thinners, a vena cava filter is sometimes used. Your doctors also look for the cause, such as recent surgery, immobility, cancer or a clotting disorder.
Cost and insurance
Health insurance can cover these procedures, subject to your policy terms. The cost depends on the hospital, the devices used and the length of stay, and is explained once the plan is made after consultation and a review of your scans. Cashless treatment can be arranged with major Indian health insurers and TPAs, and credit treatment is available for CGHS and Singareni beneficiaries. Eligibility is confirmed after a policy check.
Frequently asked questions
- Is catheter thrombectomy better than clot-dissolving drugs?
- In a randomised trial against catheter-directed thrombolysis, thrombectomy had fewer clinical deteriorations and less ICU use, with similar deaths and bleeding [4]. It is not a replacement for blood thinners, and the choice depends on the patient.
- Who is suitable for thrombectomy?
- Selected people with large clots and strain on the heart, especially when clot-dissolving drugs are risky. A PE response team decides, using your scan and condition [1].
- Are FlowTriever and Lightning different?
- Both are large-bore aspiration devices that remove clot through a catheter. Each has its own catheters and suction system. The choice depends on the clot and the operator's experience.
- Will I still need blood thinners?
- Yes. Thrombectomy removes clot but does not stop new clots from forming, so blood thinners usually continue for months.
- What are the warning signs of PE?
- Sudden breathlessness, chest pain, fast heartbeat, coughing blood, or fainting, sometimes with a swollen painful leg. Go to an emergency department immediately.
References
- Konstantinides SV, Meyer G, Becattini C, et al. 2019 ESC Guidelines for the diagnosis and management of acute pulmonary embolism. Eur Heart J. 2020;41(4):543-603. Read the source
- Tu T, Toma C, Tapson VF, et al. A prospective, single-arm, multicenter trial of catheter-directed mechanical thrombectomy for intermediate-risk acute pulmonary embolism: the FLARE study. JACC Cardiovasc Interv. 2019;12(9):859-869. Read the source
- Sista AK, Horowitz JM, Tapson VF, et al. Indigo aspiration system for treatment of pulmonary embolism: results of the EXTRACT-PE trial. JACC Cardiovasc Interv. 2021;14(3):319-329. Read the source
- Jaber WA, Gonsalves CF, Stortecky S, et al. Large-bore mechanical thrombectomy versus catheter-directed thrombolysis in the management of intermediate-risk pulmonary embolism: primary results of the PEERLESS randomized controlled trial. Circulation. 2025;151(4):260-273. Read the source
Want to discuss your options?
Speak with the Clinic Seven team.