Patient guide
Too old or too unwell for prostate surgery? PAE for an enlarged prostate in older men
Told you are not fit for prostate surgery? Prostate artery embolization (PAE) is done under local anaesthesia, usually as a day-case, and studies in older men with other illnesses found it safe and effective. What to expect and who it suits.
Why older men and men with other illnesses consider PAE
- You stay awakeOnly a numbing injection, no general anaesthetic
- 7 in 10 go home the same dayIn a UK study of PAE patients
- No cutsTreated through a tiny puncture
- Serious problems are rareSeen in about 1 in 50 men in one large study
- Quick returnUsually back to normal activity in days

"Not fit for surgery" does not mean no options
Many men with an enlarged prostate are told that surgery is too risky because of their age, a weak heart, diabetes, blood thinners or other conditions. It can feel like being told nothing more can be done. That is not true.
Medicines help many men, and they are the first step. When tablets are no longer enough, or cause side effects, and an operation is not a good idea, prostate artery embolization (PAE) is a gentler option that a growing number of men are choosing.
What makes PAE gentler
For a man who worries about the strain of an operation, the difference is in how it is done:
- Local anaesthesia. In a randomised trial, PAE was done under local anaesthesia, while TURP needed spinal or general anaesthesia [1].
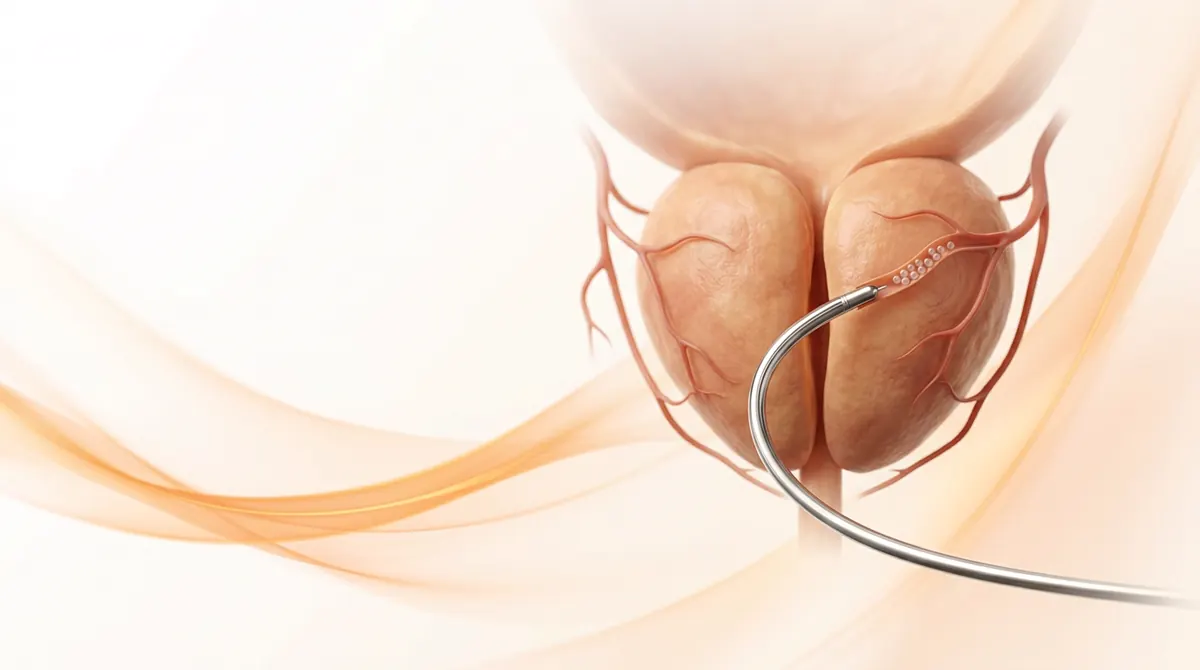
- No cutting and nothing removed. It is done from the arteries through a tiny puncture in the wrist or groin.
- Usually no overnight stay. In a UK register, 71% of PAE procedures were done as day-cases or outpatient visits. 80% of TURP patients needed at least one night in hospital, and most needed two [2].
- Fewer problems overall. In a randomised trial, there were 36 side effects after PAE and 70 after TURP in the first 12 weeks [1].
What studies found in older and higher-risk men
PAE has been studied in the men who are hardest to treat. The numbers are from smaller studies, so they are a guide and not a promise.
| Who was studied | What the researchers found |
|---|---|
| 43 men not fit for surgery, living with a catheter [6] | The catheter came out for about 8 in 10 of those treated (33 of 41), and the prostate shrank by about a fifth. The researchers called PAE safe and workable for these men. |
| 158 older men with several other illnesses (average age 74) [3] | The researchers concluded that PAE was a safe and effective treatment. The prostate got smaller, typically by about 19 mL. |
| 34 men with high-risk BPH [4] | PAE was completed in all 34. No serious complications. Symptoms, prostate size and the amount of urine left in the bladder improved at 1 and 6 months. |
| 478 men in an international study (average age 70) [7] | About 1 in 9 had any side effect (11.5%) and about 1 in 50 (2.1%) a serious one. Symptom scores fell from 21.8 to 11.2 two years later. |
| Review of 9 studies in men aged 75 and over, 1,099 men, average age 79.8 [8] | PAE, Rezum and UroLift all gave real symptom relief with acceptable safety. Serious complications in about 2 in 100 men treated with PAE (2.1%). Most procedures could be done under local anaesthesia. |
| 216 men across 17 UK centres [2] | Serious problems were rare: 1 man had a serious infection, 1 needed a blood transfusion, and 4 had a collection of blood (a bruise) in the groin. |
What we check before we say yes
We want PAE to work for you, so the consultation is thorough. In one large study of 383 men, men with diabetes, a past stroke or heart attack, or leg artery disease did slightly less well than others [5]. That does not rule you out. It is one of the things we weigh up when we plan treatment.
- Your prostate ultrasound or MRI, PSA and urine flow results
- Your heart and blood vessel health, kidney function and current medicines, including blood thinners
- A scan of the arteries to the prostate. Some men have twisted or hardened arteries that make PAE difficult, as happened in 2 of the 43 men not fit for surgery [6]
- What you want most: to avoid a catheter, to sleep through the night, to keep things as they are
Start with your symptom score
Our free prostate symptom score (IPSS) takes about two minutes. It tells you whether your symptoms are mild, moderate or severe, and you can send the result to our team to talk through your options.
Frequently asked questions
- Is PAE safe for older men with other illnesses?
- In studies of older men with several other illnesses, PAE was found safe and effective [3, 6], and in a UK register of 216 men serious problems were rare [2]. Safety still depends on you, which is why we check your health and scans first.
- Do specialist societies support PAE?
- Yes. The Society of Interventional Radiology's 2026 practice guidance, written by interventional radiologists, states that PAE has gained a place in multiple guidelines, including the American Urological Association's most recent, as a viable option for urine symptoms from BPH. It also sets out how to choose patients [9]. Whether it suits you is decided at the consultation.
- Do I need a general anaesthetic for PAE?
- No. In the randomised trial, PAE was done under local anaesthesia, whereas TURP needed spinal or general anaesthesia [1].
- Will I have to stay in hospital?
- Usually not. In a UK register, 71% of PAE procedures were day-cases or outpatient visits, compared with 80% of TURP patients who needed at least one night in hospital [2].
- Can I have PAE if I take blood thinners or have heart disease?
- This is decided case by case. We review your medicines and heart health at the consultation. Heart and blood vessel disease was linked with slightly less benefit in one study [5], so we plan carefully.
- Where can I get PAE in Hyderabad?
- Dr. Nagateja Bonala offers prostate artery embolization at Clinic Seven. Bring your prostate ultrasound or MRI, PSA, blood reports and medicines list to the consultation.
Check your prostate symptom score
References
- Abt D, et al. Comparison of prostatic artery embolisation (PAE) versus transurethral resection of the prostate (TURP) for benign prostatic hyperplasia: randomised, open label, non-inferiority trial. BMJ. 2018;361:k2338. Read the source
- Ray AF, et al. Efficacy and safety of prostate artery embolization for benign prostatic hyperplasia: an observational study and propensity-matched comparison with transurethral resection of the prostate (the UK-ROPE study). BJU Int. 2018. Read the source
- Zorzi F, et al. Prostatic Artery Embolization in Elderly Comorbid Patients with Benign Prostatic Hyperplasia: Safety, Efficacy, and Predictive Factors of Clinical Failure. J Pers Med. 2025. Read the source
- Wang K, et al. Efficacy and Safety of Prostatic Artery Embolization in the Treatment of High Risk Benign Prostatic Hyperplasia and its Influence on Postoperative Life Quality of Patients. 2022. Read the source
- Frandon J, et al. Efficacy and safety of prostate artery embolization for patients with lower urinary tract symptoms and indwelling urinary catheter: A retrospective multicenter study. Diagn Interv Imaging. 2022. Read the source
- Rampoldi A, et al. Prostatic Artery Embolization as an Alternative to Indwelling Bladder Catheterization to Manage Benign Prostatic Hyperplasia in Poor Surgical Candidates. Cardiovasc Intervent Radiol. 2017. Read the source
- Sapoval MR, et al. Two-Year Outcomes of Prostatic Artery Embolization for Symptomatic Benign Prostatic Hyperplasia: An International, Multicenter, Prospective Study. Cardiovasc Intervent Radiol. 2024. Read the source
- Ozervarli MF, et al. Minimally invasive treatments for benign prostatic hyperplasia in patients over 75: a systematic review. World J Urol. 2025. Read the source
- Mouli S, et al. Society of Interventional Radiology (SIR) 2026 Practice Guidance Document for Prostatic Artery Embolization. J Vasc Interv Radiol. 2026. Read the source
Want to discuss your options?
Speak with the Clinic Seven team.